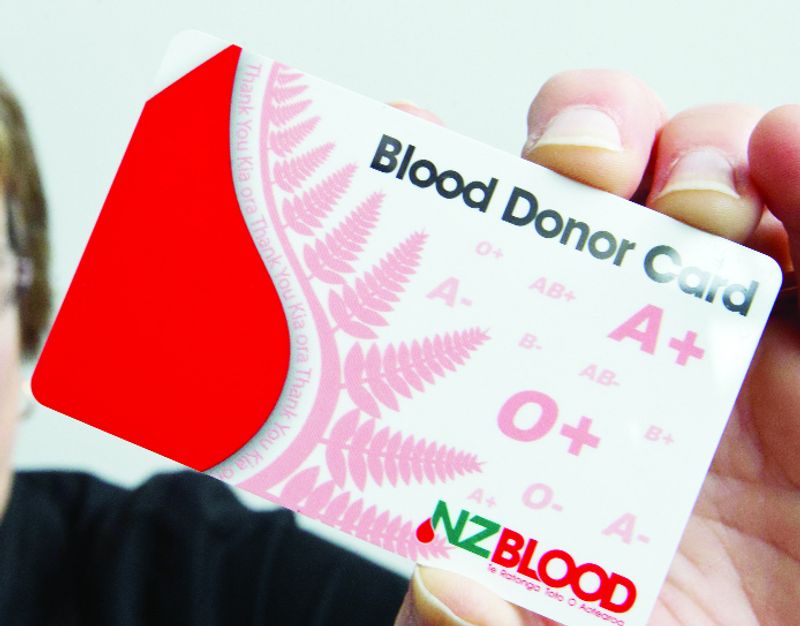
In Jammu, a person who has freely donated blood at a Government hospital and carries a donor card as proof of that service can still be turned away when they try to use that card to obtain a unit of blood for a patient admitted to a private hospital. On paper, the system speaks of “priority for donors.” In practice, at the blood-bank counters of major Government hospitals, the message that families often hear is starkly different. The card may be acknowledged, but the blood will not be issued for a private-hospital patient, or it will be issued only if the family produces replacement donors. This gap between policy intent and ground reality is not merely an administrative inconvenience; it undermines trust in the blood-donation ecosystem, penalises voluntary donors, and forces vulnerable families into last-minute scrambling for donors at a time of medical crisis.
India’s national blood policy and related guidelines are clear on several principles that should, in theory, protect donors and patients alike. The National Blood Policy (2007) states that the practice of replacement donation shall be gradually phased out in a time-bound programme and that there shall be no coercion in enrolling replacement donors. National standards for blood centres direct that blood banks should move towards 100% voluntary, non-remunerated donation, discontinue the policy of charging deposits against replacement, and ensure that patients are not denied blood in emergency situations. Within this framework, several states and institutions have introduced donor-card schemes as an incentive. A person who donates blood receives a card that entitles them, and often their immediate family, to priority access and a free unit of blood when needed.
In Jammu and Kashmir too, blood banks have promoted voluntary donation and issued special donor cards suggesting that voluntary donors will be able to “receive blood very easily, if the need arises” or in case of an emergency. This approach creates a reasonable expectation that if you donate, you and your family should find it easier, not harder, to access blood when you need it. Yet the lived experience of many families in Jammu tells a different story. A donor who has given blood multiple times at a Government hospital, proudly holding a card issued by that very institution, approaches the blood bank with a requisition from a private hospital where a relative is admitted. The counter staff may check the card, confirm its authenticity, and then explain that it cannot be used to take blood “out” for a private-hospital patient. Some banks say the card is valid only for in-patients of that Government hospital; others quietly signal that the file will move faster if the family brings replacement donors, even though national policy says replacement should not be mandatory and should be phased out.
The result is a cruel puzzle. The very people who have strengthened the blood supply through voluntary donation find themselves at the back of the queue or forced into the same replacement-donor treadmill that policy claims to be ending. This is not merely a matter of procedure; it has tangible consequences. Families delay transfusions while they search for donors, clinicians face ethical distress as they watch treatable patients deteriorate for want of blood, and the moral message sent to the community is blunt: your voluntary donation earns you a card, but not a guaranteed right to blood when your loved one is in a private hospital. The gap is especially sharp in a city like Jammu, where a significant share of care takes place in private facilities and where major Government blood banks-attached to GMC, SMGS, Gandhi Nagar, and others-are the primary pools of safe, screened blood received from donors.
This disconnect does not arise from a single villain but from a mix of ambiguous rules. National guidelines emphasise voluntary donation and discourage replacement donation, but they stop short of prescribing a uniform, enforceable rule that every Government blood bank must honour donor cards for private-hospital patients. In that vacuum, blood banks craft their own standard operating procedures, often shaped by fears of stockouts, complaints from other patients, and liability concerns if blood is issued “outside” and something goes wrong. Donor cards themselves are frequently worded in vague terms-promising “priority” and “easy access” without clearly stating whether they are redeemable for private-hospital cases, for how long, and for which categories of relatives.
Addressing this problem requires action on multiple fronts. First, the Government of Jammu and Kashmir must issue a clear, written policy specifying that donor cards can be used for patients admitted to private hospitals as well. The policy should also outline the mandatory documentation requirements and any reasonable blood-testing charges. Second, blood banks need standardised forms and workflows to ensure that life-saving blood requests from private hospitals, supported by valid donor cards, can be processed without unnecessary negotiations at the counter. Third, supervisory bodies must monitor compliance, investigate complaints of refusal, and ensure that the national principle of “no coercion for replacement” is not quietly overturned by local practice. Finally, the local community needs transparency and full support after voluntary donation, so that the promise of “priority for donors” is not reduced to a slogan. Until this gap is closed, Jammu’s blood-donation system will continue to send a contradictory message: “Give freely, but do not expect that your gift will reliably come back to you when you need it most.”
(The author is President, Young Blood Association, J&K)